
HealthNews
14 reported sick after visiting McMenamins Anderson School pool in Bothell this summer

Public Health — Seattle & King County has completed its investigation into a cryptosporidiosis outbreak linked to the pool at McMenamins Anderson School in Bothell.
Fourteen people reported becoming ill after swimming at the pool on Aug. 29 or Aug. 30, according to public health officials.
Their symptoms began between Sept. 3 and Sept. 5 and included nausea, diarrhea, abdominal cramps, and fever, according to the report.
No hospitalizations or deaths were reported, Public Health — Seattle & King County said.
Five people who became ill were tested, and four were diagnosed with cryptosporidiosis, an illness caused by the parasite Cryptosporidium, according to Public Health — Seattle & King County.
The parasite can cause watery diarrhea and other gastrointestinal symptoms.
Health officials said they suspect someone infected with the parasite used the pool and spread germs to others.
The parasite is highly resistant to chlorine and can survive for several days in even a well-maintained pool, officials said.
Public Health inspected the facility Sept. 21 and found no violations.
Officials said the pool was well-maintained and followed King County health and safety requirements.
Investigators also reviewed fecal incidents at the facility because contaminated pool water can spread the parasite.
The pool operator did not report any fecal incidents on Aug. 29 or during the 10 days before that date, according to Public Health.
Officials interviewed six people who became sick and reviewed Cryptosporidium education and cleanup procedures with the facility operator.
They also reminded the operator that guests are not allowed to use the pool if they have had vomiting or diarrhea within the previous two weeks.
The outbreak appears to be over, Public Health said.
The “North Shore Lagoon Swimming Pool” is open to the public in one-hour sessions, according to the McMenamins Anderson School website.
There is a pool admission price listed; Bothell residents are free with current proof of address, the website states.
Officials recommend that people stay out of public pools for at least two weeks after diarrhea or vomiting has completely stopped, shower with soap before entering a pool, and avoid swallowing pool water.
HealthNews
My husband’s anxiety has always taken one particularly strange form. But things just escalated beyond what I can stand.

Each week, exclusively for Slate Plus members, Prudie discusses a new letter with a fellow Slate colleague. Have a question for Prudie? Submit it here.
Dear Prudence,
My husband has pretty severe anxiety/OCD, mostly concentrated on health and medical situations. Nothing can be a minor illness—it is a sign of something much more serious and sinister. He is on medication for it and he reports that it helps, but I do think he most likely needs a higher dosage or something for more support. He regularly (probably four times a year) becomes convinced he has an STI of some type due to relatively benign symptoms like a rashy dry skin patch or a bruise near his genitals. When this happens, he usually asks me a couple times if I think he could have (fill in the blank STI). I usually just ask if he’s had sex with anyone else or thinks I have, he says no, and I say “then I don’t see how you would have an STI” and refuse to answer him on it again (original advice of his doctor/counselor when starting OCD treatment).
But this last time has been different.
About one week after travelling for work, he asked again about what was definitely an eczema patch. I answered as I usually do, but a couple days later he told me he was really worried about it and was going to contact his doctor to order blood testing for STIs. I said I thought that was unnecessary. He got the tests done and everything was negative, so he went right back to his usual self.
But now I’m convinced he cheated on me on his work trip. Since starting his medication, he has never needed more than a verbal confirmation that he wouldn’t have an STI. I have never thought he would cheat on me, but he did go out with people one night, and I know they all drank quite a lot. When he travels, he normally calls me either before bed or in the morning while I’m getting ready for work and he didn’t this time, instead texting that he was out and then around lunchtime the next day saying it had been a rough night/morning. What would you recommend as the best way to approach him on this? I’m worried he’s going to just explain it away as his OCD being more severe this time and needing more reassurance, but I also think this is a reasonable reaction on my part. I feel like I’m always supporting him through the things he struggles with and the one time I have a concern (that actually has some evidence to it!), it’s just going to get brushed off.
—Now I’m Anxious
Jenée Desmond-Harris: I don’t know why I initially misread this as being about her brother (I truly pulled that out of nowhere) and I was so happy to say “You don’t have to worry about this! It’s not your business.” Now that I have my facts right, things have become a lot heavier. Yeah, this is totally her business.
Lizzie O’Leary: I am kind of stunned by the lack of trust here. And maybe that’s not fair, but it’s wild to be repeatedly asking your spouse if they have had sex with other people, even if most of that is coming from a place of mental illness! I think that is the place these two need to start.
Jenée: Right, if you’re going to have ideas about STIs that don’t have a basis in reality, you may as well take the irrational thinking all the way and imagine that you got them from a toilet seat or something.
I agree with you that the lack of trust is a big problem. And actually, it would be helpful for the letter writer to strip away all the mental health history and ideas about what kind of support she’s owed and how her husband will receive her concerns and focus on the core issue: She thinks her he cheated! And that he’ll lie about it! So maybe the goal is not to get him to take that concern seriously, but to decide what it means for whether she wants to be in this marriage.
Do you think a digital snooping investigation is warranted here? Because I know nobody wants to get divorced based on a weird feeling alone.
Lizzie: I think some counseling is warranted. Digital snooping is so messy, and even if she finds some proof of affair, getting it that way is horrible and upsetting. And puts her on the back foot. I think she needs to tell her spouse how she feels, AND that she is so turned around by all of this that she doesn’t know whether to trust him. It sucks, but I don’t think there is a way to be like “hmm yeah I think you may still be lying though,” without really probing what that means about the marriage.
Jenée: Well, I’m glad there’s one reasonable and mature person in this chat. I’m not sure why I suggested the 19-year-old approach. Counseling would be great because maybe things could be repaired (I know an Esther Perel or Dr. Orna wouldn’t see it as a dealbreaker even if the cheating allegations were confirmed—maybe there’s a better relationship on the other side of this!) and if not, it would be nice to have someone to guide the couple through wrapping things up. Oh, and maybe the therapist would suggest more individual work for the husband, which could lead to a medication adjustment, which could lead to STI worries no longer playing such a big role in this relationship.
Lizzie: Yeah, at the bare minimum, repeated allegations of cheating over random rashes are not a great way to live! Jenée, maybe if I see Dr. Orna in the neighborhood walking her little dog, I should ask her? Obviously I will not, because I am a New Yorker and we mind our own business. But still. LW, this is not about this one-time accusation, it’s about the fact that your marriage needs more support! Dealing with mental illness can be incredibly difficult in a relationship, but I don’t think it’s impossible. You two just need to be able to trust each other. And right now you can’t.
Jenée: Yes, please. Dr. Orna and her dog have enough couples to deal with.
Anyway, letter writer, sorry to pass the buck to a therapist here, but it really is the best way forward. Pretend you never heard me mention snooping. I wish you a future with more trust and fewer suspect rashes.
HealthNews
Sleep Research May Shift Thinking on ADHD

Generally speaking, people with ADHD tend to have trouble sleeping. But new research suggests that sleep problems might not merely be a symptom of the condition but at the root of what’s causing it, reports the Washington Post. A perspective paper (not a clinical trial) in Frontiers in Psychiatry sees a strong correlation between ADHD and people with dysfunctional circadian rhythms, which govern when we sleep and wake. Physician Brandon Luu and co-author Nicholas Fabiano pull together “convergent” evidence that people with ADHD often run on a significantly later internal schedule: up to 78% show delayed sleep timing, with melatonin kicking in much later than is normal.
“In other words, some people with ADHD may not simply be ‘bad at going to bed,'” observes a post at Proactive Psychiatry. “Their internal clock may actually be shifted later.” The researchers urge clinicians to routinely screen for circadian disruption and use sleep tracking as a cheap, low-risk tool for ADHD. The wider field is moving that way, too: Psychiatrists are probing whether misaligned body clocks underlie conditions from depression to schizophrenia, and testing fixes like morning light therapy, structured wake times, and timed exercise to “phase shift” patients closer to society’s demands, notes the Post. The thinking is that in at least some cases, recalibrating the clock could ease the mind.
Read These Next
Jewish groups denounce Mamdani’s
Lawyer shares new details of
Alan Alda’s first sign of Parkinson’s
Just 2 toilets on plane with nearly 300 aboard
HealthNews
GLP-1s linked to a gross side effect in nails: study

Ozempic and Mounjaro can cost an arm and a leg — and maybe a fingernail.
A new study found that people on GLP-1 drugs were nearly 25% more likely to experience a nail disorder than those not on the drugs.
And one particularly squirm-inducing problem was over four times more likely to appear in GLP-1 users.
The new study, presented at the European Academy of Dermatology and Venereology, found that 39% of GLP-1 users reported nail detachment — when the finger or toe nail separates from the nail bed — compared to just 9% of controls.
Once it’s detached, the nail can’t be reattached. It’ll take several months or over a year to regrow.
But that’s not all. Researchers report two thirds of GLP-1 users report at least one nail disorder, including nail discoloration — which appeared 2.7 more frequently in those on the meds.
“Until now, nail changes associated with GLP-1 therapies had essentially been anecdotal,” said study author Charles Taïeb.
Do GLP-1s cause nail problems?
In trials, GLP-1s have shown to cause up to 22% weight loss — while real-world loss is more around 2-8% in a year.
That weight loss can cause nail problems, though, from slower growth to brittle nails. This is connected to nutritional deficiencies as a result of less eating, and dehydration.
Researchers of the new study can’t say for sure whether it’s the meds causing nail issues, or primary effects like weight loss.
While researchers did try to adjust the results accounting for existing dermatological conditions, nutritional deficiencies, and weight loss, nail detachment and discoloration still showed up two to three times as often with GLP-1 users.
“Our findings show a clear association, but they also underline an important point: not everything that happens during GLP-1 treatment is necessarily caused by the treatment itself,” Taïeb said.
Nail and hair loss
A companion study with the same participants in the first showed that hair loss was also significantly higher in those on a GLP-1 drug.
Unusual hair loss (noticeable shedding) was reported by 50% of GLP-1 users compared to 34% in those not on the drug.
Loss in volume or density (overall less hair that remains) was more than twice as common in those on the jab, and scalp redness was around three times as common.
Hair loss on GLP-1s are a known phenomenon. Experts say that it’s “almost always” temporary and a reaction to weight loss and rapid physical changes.
Authors of this study believe that something more than weight loss is at play, though. They note that hair loss was usually accompanied by itching, redness, or scaling — a sign that there’s “an inflammatory component” at play.
“Scalp inflammation was the rule rather than the exception, which clinicians do not currently look for and which may be treatable,” explained author Dr. Bruno Halioua. Doctors can prescribe special shampoos and topical medications to address inflammation on the scalp.
Authors stress these new results should be for “awareness rather than alarm.” Hair and nail loss, at the end of the day, is aesthetic and temporary, while weight loss has a huge long-term impact on many aspects of health.
“These changes are frequent, usually benign, and are not a reason to stop an effective treatment on one’s own initiative,” Halioua said. “Anyone who notices hair shedding, an itchy or red scalp or nail changes should mention it to their doctor rather than discontinue therapy.”
HealthNews
Covid, flu, West Nile virus, and plague
As we recover from a hot week, today’s focus is back on infectious diseases. We’ll start with Covid, one of our most familiar bugs and end with plague, a rare but serious disease. (Spoiler: the risk to you right now is essentially nil.)
Covid-19 bowing out slowly
We’re continuing to see elevated but declining Covid-19 activity across the state. The 2026 peak in wastewater levels was about three weeks ago, which is consistent with last year’s pattern.
We should expect elevated Covid-19 activity for a few weeks. Which matters more in light of the recent arrival of flu.
Flu season under way
On the flu front, transmission rates are increasing day by day. The season took off almost two months ahead of our usual late November timing. This graph shows emergency department visits for Covid-19 are declining as flu increases. You can also see here that RSV, which is the third main respiratory virus we focus on in California, remains flat. It usually increases in late October or November.
I expect in the next couple weeks these top lines will cross, and flu will take its usual role as the main contributor to serious respiratory illness in California through fall and winter.
Combined risk: Because Covid-19 will also remain active for a few weeks, our risk of being exposed to both viruses when we’re out and about is elevated. If you’re at higher risk of severe disease, consider masking up in indoor public spaces.
Flu vaccine uptake: The single most important thing we can do to protect ourselves from the flu is to get the vaccine, and preliminary data show a lot of us know that. Nearly 3 million Californians have already gotten this fall’s flu shot, which is about 400 thousand more than had it by this time last year. So hopefully everyone’s getting the message that it’s game on for flu. Vaccines are available in pharmacies and clinics across the state.
West Nile virus still rising
We’re continuing to see unusually high levels of West Nile virus (WNV) across the state. Remember we’re only infected through mosquito bites, so our risk depends on the burden of the virus in the mosquitoes around us, and our likelihood of getting bitten.
Record warm temperatures through winter, spring, and into summer have supported larger mosquito populations, and also allowed the virus to reproduce more quickly.
Right now we’re at 252 human cases, about five times higher than at this time last year, with 19 deaths.
Almost all parts of the state are impacted. Thirty-eight counties have reported WNV activity, and 23 have human cases. Adjacent Los Angeles and Orange counties have the highest regional burden, with a combined 143 cases and 8 deaths.
There’s no vaccine and no treatment, so it’s mainly about bite prevention.
Remember the four Ds:
Use insect repellent that contains Deet or picaridin.
Cover your arms and legs at dawn and at dusk, when the mosquitoes that carry West Nile are most active.
Drain any standing or stagnant water around your property.
Plague
Finally, plague. You’ve probably seen news about a plague death in a researcher working in a lab in Russia. (To get up to speed, see YLE National’s FAQs from earlier this week.) It’s definitely headline grabbing, but we need more information before knowing what to make of this.
In the meantime it’s a good time to remember what we know about plague. For Californians, plague is not unfamiliar—the bacterial disease is actually endemic to our state. Here’s a refresher.
Is this The Plague? Yes, this is the same bacteria (Yersinia pestis) behind the Black Death that killed about one third of people in medieval Europe. But our situation is very different today.
It’s extremely rare. In 2025, El Dorado County reported a human plague case. The patient was probably infected from a flea bite while camping in South Lake Tahoe. Two people were infected in 2015 after exposure in Yosemite National Park. Nationwide, we see an average of about seven cases per year.
We know how to diagnose and treat it. Antibiotics can treat it, and doctors and nurses in endemic regions are trained to spot and manage it. Untreated, about two in three people with plague die. With treatment, mortality drops to about one in ten.
It usually spreads through fleas after contact with infected rodents, like chipmunks, prairie dogs, mice, rats, or squirrels. Pets, especially cats, can also bring the infection into homes if they roam outdoors. Person to person spread, even in the pneumonic (respiratory) form of the plague (the form the Russian lab worker is suspected to have died from) is very rare. Transmission of plague between people requires prolonged close contact.
It’s regional. In the U.S. plague is found in the rural West, including California, where the bacteria circulates naturally in wild rodents. Urban rats have not been found to carry plague in California.
Note: all cases reported in the East had recently traveled from the West.
Personal note: When I was in the Indian Health Service in Arizona, I took care of a woman with pneumonic plague who was infected by her cat. A smart doc I worked with recognized the signs and started antibiotics right away. She survived, and the source was traced to an infected prairie dog colony near her house.
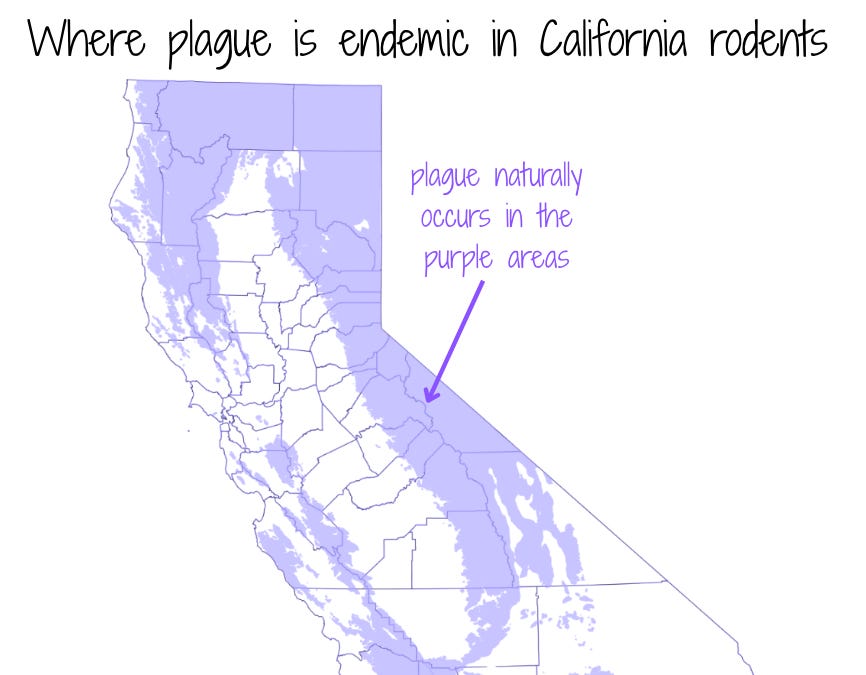
The California Department of Public Health tests rodents to track plague risk. This map shows where rodents carry antibodies to the bacteria that causes plague—a sign they’ve been exposed.
Back to the Russia case… The most important thing I’m looking for right now out of Russia is any additional cases, because the most concerning scenario is if the bacteria has been modified in a lab toward a more contagious form—which I doubt. If person-to-person contagiousness has changed, then we might see true outbreaks with more cases, and would need to prepare, over time. But that’s theoretical, and not something Californians need to worry about until we know more. I’ll follow this and keep you updated.
Preventing plague in California. Plague prevention is most relevant when we’re in an endemic area doing outdoor activities.
Never touch or feed wild animals.
Keep pets leashed to prevent contact with rodents.
Use insect repellent on socks and clothing to prevent flea bites.
Keep fleas off of your pets by applying flea control products year-round.
Plague exists in our rural areas, but the risk remains extremely low. Keep enjoying our great outdoors (and let me know your great camping spots!), and take simple precautions to stay healthy.
I’ll follow the situation across the sea and provide relevant updates.
Poll: AI and health
I recently joined a Stanford forum on trust and safety in the use of AI in health, and I came away acutely aware that the rapid evolution and adoption of AI is partly a matter of public health. As we navigate where the public health voice belongs in this conversation, I’d love to know what you see as some of the most pressing concerns. Please put any others in the comments.
Bottom line
That’s your roundup for this week! Don’t forget your up-to-date Covid-19 and flu vaccines are in pharmacies and clinics now.
Love,
Matt
Dr. Matt Willis is the author of Your Local Epidemiologist in California. A California native, he’s served as a primary care physician, CDC epidemiologist, and public health officer for Marin County, where he guided the pandemic response. He lives in Marin with his family and their dogs, Teddy and Ramona.
HealthNews
It can keep cancer in remission. Why is no one talking about it?

Lee Colker powered on an iPad in the basement of his Pittsburgh home and logged into a virtual exercise session with Olivia Masten, a trainer who specializes in working with cancer patients.
Colker, 66, had been dealing with unpredictable fatigue and brain fog since beginning a clinical trial for metastatic kidney cancer this year. When staff at the University of Pittsburgh Medical Center told him an exercise program could improve his energy, he jumped at the opportunity. “That was a clincher for me,” he said.
The program is part of a growing effort around the country to help cancer patients exercise, as the benefits of doing so become increasingly clear.
Observational research has long suggested that exercise improves cancer survival, particularly for breast cancer patients. Last year, a landmark randomized controlled trial showed that colon cancer patients who participated in a structured exercise program with a trainer-coach over three years were less likely to have their cancers come back and had a better quality of life. Among those in the program, 90% were alive after eight years, compared with 83% in the control group.
A later study showed the program, which altogether cost $3,000 per person, also saved the health system money — “a home run,” said Dr. Scott Ramsey, a cancer researcher and health economist at the Fred Hutch Cancer Center in Seattle.
That combination of benefits is rare among cancer therapies: The new pancreatic cancer drug daraxonrasib, for example, costs $480,000 annually, has unpleasant side effects and, while it prolongs life by several months, does not increase overall long-term survival.
“If we had a drug with this magnitude of benefit, it would immediately become standard of care and funded” by insurance companies, said Dr. Christopher Booth, an oncologist and professor at Queen’s University in Kingston, Ontario, and the leader of the exercise trial.
While guidelines now recommend that oncologists help colon cancer patients achieve at least 150 minutes of moderate to rigorous exercise per week, there’s not yet an insurance pathway to pay for these programs — a major barrier to rolling them out more widely.
“You can tell patients that if you do this, you may survive longer,” Ramsey said. But unfortunately, he added, “we just don’t have the infrastructure.”
Current programs are largely limited to major cancer centers and dependent on philanthropy or individual out-of-pocket payments to cover costs, leaving poorer patients and those who live far from these centers without access.
Dr. Jeff Meyerhardt, a gastrointestinal oncologist at Dana-Farber Cancer Institute in Boston, refers his patients to the hospital’s center for alternative therapies, where they can consult with a trainer and access in-person and online exercise classes. But the trainer can’t continue supporting patients over time.
At the University of California, San Francisco, doctors refer eligible patients for physical therapy and rehabilitation, which can be reimbursed by insurance, while many YMCA branches offer a free or low-cost 12-week program for cancer survivors.
Improving outcomes among cancer patients isn’t as simple as telling them to exercise more. Often, people need support to work up to and stick with a rigorous regimen, said Kathryn Schmitz, an exercise oncology researcher at UPMC Hillman Cancer Center. “Exercise is not just biology,” she said. “It is also behavior.”
Schmitz is the founding director of Moving Through Cancer, the program in which Colker is participating. It is tailored to each patient: Some need more support, while others “are well enough to go out and play some pickleball,” she said.
Kimberly Barker, 68, suffered from low back and hip pain and fatigue after treatment for bladder and uterine cancer. A quilter who used to bicycle with her husband on trails near their home in Butler County, Penn., Barker lost the motivation to do the things she loved.
“I was just so tired, no energy, no stamina,” she said.
She met with Masten, the trainer, once a week for 12 weeks, and also did the suggested exercises between meetings. She continued doing them after the program ended, and now feels back to her normal self. She and her husband have resumed their bike rides.
Because of the success in people like Barker, UPMC has decided to offer the program through its employee health plan for breast cancer patients beginning next year.
The health system will be the first in the country to offer insurance coverage for exercise oncology, Schmitz said. She and her colleagues argued for it based on randomized trials that showed it saved costs by reducing hospitalizations, emergency room trips and unplanned office visits.
“This UPMC rollout is a giant experiment,” Schmitz said. If it’s successful, the hospital plans to expand it to all cancers in 2028. Schmitz also pushed to incorporate exercise into standards that cancer hospitals must follow to receive certain accreditation, which will happen later this year.
“This is no longer just something that would be nice to have,” Schmitz said. “This is a therapeutic intervention, it needs to be done — and it needs to be done for all patients.”


Tech stocks drop after report that OpenAI’s revenue is lower than expected
Tech stocks dropped on Thursday after a news report that OpenAI’s annualized revenue is about $20 billion less than previously...


US freezes Microsoft, Adobe, Infosys green-card applications over alleged fraud
The twin actions mark the broadest strike yet against skilled-worker immigration programs — potentially cutting off a common path to...


Google brings agentic AI to Gemini, starting with businesses
At a Google Cloud event on Thursday, the company announced it’s bringing its Gemini AI into the agentic age, with...


Nvidia, Oracle, other AI stocks sink on OpenAI revenue report
Shares of Nvidia , Oracle , CoreWeave and other artificial intelligence names sank lower on Thursday after the market learned...
Why its DEI lending policies are under fire
The Trump administration is investigating a Wells Fargo program to increase the homeownership rate of Black Americans, signaling a sharp...
Micron Stock Drops. Why Samsung’s Record Profit Didn’t Give It a Lift.
You are now leaving Barron’s website By clicking on the “Proceed” button below, you will be redirected to a third-party...
Stock Market Today: Oil Rises, Nasdaq Slips After Fresh Tanker Attack
Oil prices fell from their daily highs after President Trump posted on social media that the U.S. is having “productive...


Fired OpenAI employees raise concerns over AI safety, monitoring
Newly awarded Nobel Prize-winning physicist Francis Halzen credited artificial intelligence with helping researchers uncover new insights into the Milky Way,...


Diversity Now Seen as “Optional”
When #Emmyssowhite began trending after white actors swept the lead and supporting acting categories during the Sept. 14 ceremony, it...


Taylor Swift to Perform at Academy Museum Gala
Taylor Swift is set to perform at the upcoming Academy Museum Gala. The evening, taking place on Oct. 17, serves...
-

 Sports1 week ago
The Case Keenum game? Veteran QB delivers for Chicago. Bears vs. Eagles takeaways
-

 Entertainment6 days ago
‘Verity’ Posts $4.5M Previews, ‘Digger’ $1.2M
-

 Business2 weeks ago
A 46-foot tunnel boring machine grinding 110 feet under a Virginia harbor chewed a mastodon loose from the seabed and pumped it toward land as slurry, and an operator watching the mud for metal spotte
-

 Entertainment7 days ago
Rick Devens Wins In Season 28 Finale
-

 Video7 days ago
Meta's Muse: Cute AI Agent Or 'AI Trojan Horse'? | BBC News
-

 Business5 days ago
Tesla Cybercab pressure to expand after rocky first month in Austin
-
Business6 days ago
Leaked Anthropic IPO prospectus: The US government could hurt our business
-

 Business5 days ago
OpenAI safety employee resigns, claiming the company’s ‘culture is broken’